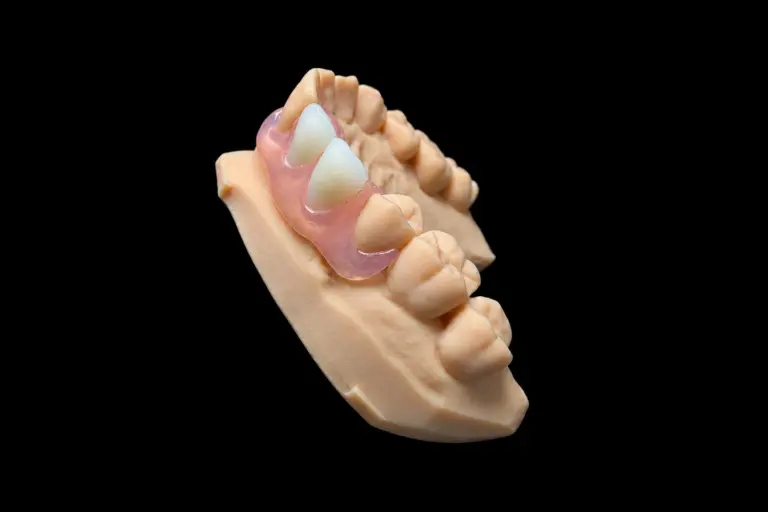
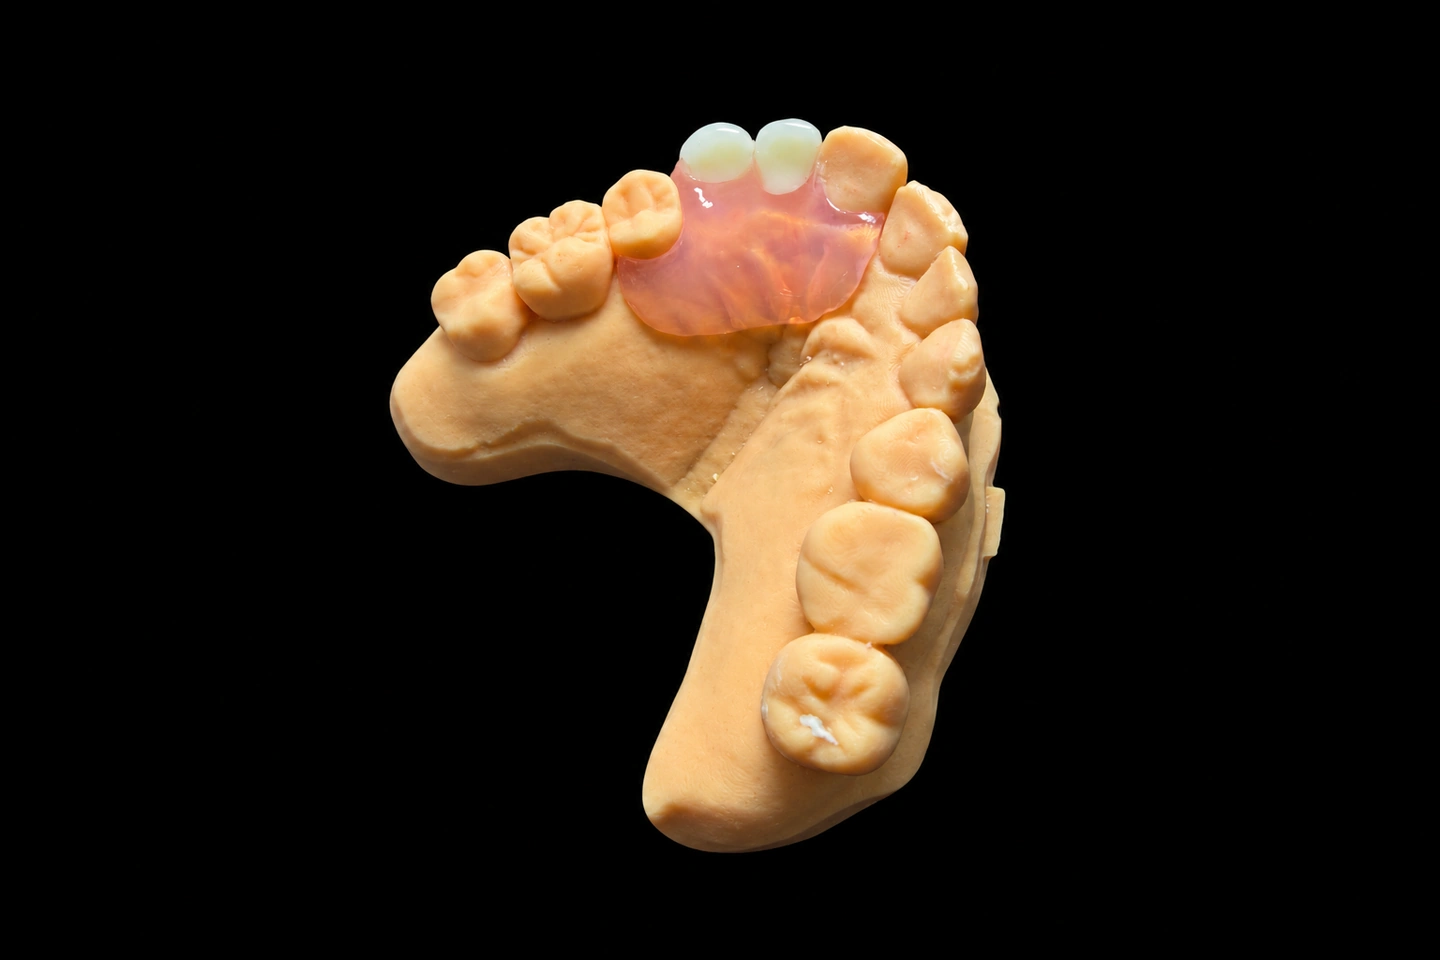
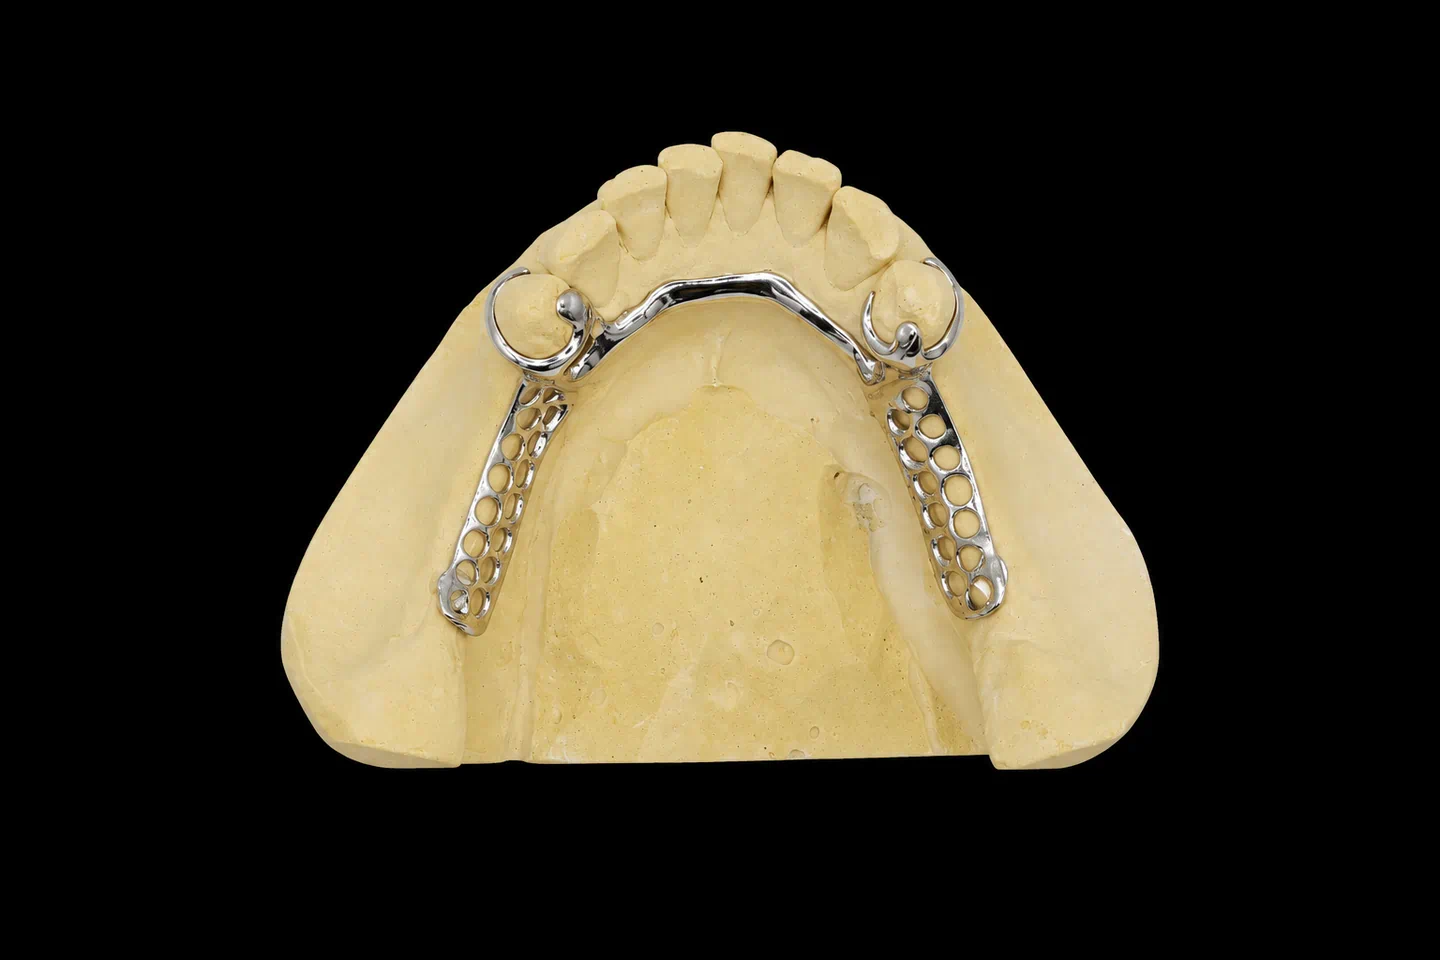
Patient Situation Before the Flexible Lower Denture
The patient behind this flexible lower denture lost #19 about eleven years ago and #30 about six years ago . Nothing ever went in either space. Over time #18 tipped into the #19 gap , and most chewing moved to the premolars . The patient finally wanted molars back on both sides, but not at any price :
There’s no metal allergy on this chart . This wasn’t about avoiding metal for its own sake.
The dentist’s notes and records showed:
What the Dentist Asked For
The Rx for this flexible lower partial denture, condensed :
The Technical Problem: One Undercut, Two Risks
Why a metal frame was hard here
A rigid part goes in on one path and can’t flex past anything. On a tipped #18, the widest part of the tooth sits high on the mesial and lingual sides . A frame has to stay above that line, which leaves a gap underneath for food and the tongue. Closing that gap means reshaping the tooth, and rests and guide planes mean more prep.
A dental CE course on non-metal clasp dentures names both of these situations: tilted teeth with a soft tissue undercut, and patients who refuse tooth modification.
Why flexible wasn't a free pass
Valplast can flex past a modest undercut. It shouldn’t be forced into a deep one, because the base has to get in and out over that tissue every day, and a tight flange there means sore spots. So the question changed. Not “will it go in?” but “which undercuts do we use, and which do we stay out of?”
Then there’s the price of no rests. With an all-flexible design, the same CE course says the base leans on soft tissue, which can lead to abutment displacement and ridge resorption, especially without occlusal stops. This patient still had tooth contacts on both sides , but the saddles themselves have nothing to stop them from sinking.
The Three Designs We Sent the Dentist
We held the case on lab day 1 and emailed the survey notes with this table:
| Option | What it needs | Good | The catch |
|---|---|---|---|
| A. Metal framework partial with rests | Reshaping on #18, rest seats on #18, #20, #29, #31 | Steadiest. Teeth carry the load | Conflicts with Rx items 1 and 2 |
| B. All Valplast, low lingual strap | No prep. Strap sits below the gum margins | Front teeth stay clear. Meets the whole Rx | Base leans on tissue. Strap flexes more than metal |
| C. All Valplast, plate over the lower front teeth | No prep. Covers the lingual of #22–#27 | More bracing across the front | Covers the gum margins, conflicts with Rx item 4 |
We said Option A would be the steadiest. The dentist went over it with the patient, who still didn’t want any drilling . The dentist picked Option B . That call belongs to the dentist. The risks were on the table, so we built it to the Rx.
How We Made This Flexible Lower Denture
Each line of the Rx turned into lab work:
| Rx item | What we did |
|---|---|
| 1 | Valplast resin only. Base, strap, and clasps as one piece |
| 2 | Used existing undercuts, with no rest seats |
| 3 | Blocked out most of the #18 undercut and kept the flange above its deepest part |
| 4 | Ran the strap’s top edge 2 mm below the gum margins |
| 5 | Ran the #20 and #29 arms low and checked them against the photos |
| 6 | Set contacts on an articulated model and marked them with film |
| 7 | Checked teeth and base against the shade photos, before and after finishing |
| 8 | Emailed design screenshots, waited for sign-off, then sent the try-in |
| 9 | Shipped the certificate with the case |
The undercut map
On this flexible lower denture, every spot got one job:
| Spot | Undercut | Job |
|---|---|---|
| #18 mesiolingual, tooth | 1.3 mm | Too deep for an arm. Blocked out |
| Lingual tissue below #18 and #19 | 2.0 mm | Blocked down to about 0.4 mm . Flange stops above the deepest part |
| #18 buccal | 0.6 mm | Retentive arm |
| #20 distobuccal | 0.5 mm | Retentive arm, kept low |
| #29 distobuccal | 0.5 mm | Retentive arm, kept low |
| #31 mesiobuccal | 0.6 mm | Retentive arm |
Why not block out all of it? A thermoplastic resin maker’s technical guide puts it simply: never block out 100%, since retention is needed. You can relieve an area during finishing, but you can’t add to it. That guide covers TCS resins, not Valplast, but the logic carried over. We left a little, and planned to ease more only if the delivery called for it.
Clasps for a lower flexible partial denture on four different teeth
A CE course page on clasp designs lists a circumferential clasp for a free-standing, mesially tipped distal abutment. That’s #18 exactly, so it got a circumferential arm, 1.2 mm thick . #31 got a standard clasp at 1.2 mm , going for its 0.6 mm undercut.
#20 and #29 show when the patient talks , so those arms stayed thin and low. The same page pairs a 1.0 mm Valplast clasp with a 0.5 mm undercut, and that’s what we used on both .
The strap under the tongue
A flexible lower denture doesn’t get much connector room. A textbook chapter on major connectors asks for 6–8 mm from gum margin to floor of the mouth for a lingual bar: top edge 2–3 mm below the margin, bottom 1 mm above the floor, at least 4 mm wide. Those numbers are written for a rigid bar. We didn’t find a published version for Valplast, so what follows is a decision for this one case.
With the dentist’s 7 mm reading , we started at 2 mm + 4 mm + 1 mm . Tight, but it fit. Since the TCS guide notes that major connector thickness controls how much these resins flex, we set the strap at 2.2 mm thick and rounded the lower edge.
A narrow space, and keeping the teeth in
The tip had shrunk the #19 space to 8 mm . A full-size molar wouldn’t fit, so we used a narrower mold for #19 and a regular one for #30 . The mismatch sits far enough back that nobody sees it .
Thermoplastic bases don’t bond chemically to denture teeth, so the teeth hold on mechanically. Grinding teeth down for tight space can lead to cracks. With 5.6 and 5.8 mm , neither tooth needed heavy shortening. Each one got retention holes, cleared of wax before injection so the resin could fill them . The fuss has a reason: Canada’s Drug Agency cites a nonrandomized study with more artificial tooth loss on flexible partials than on conventional ones after a year.
What the Try-In Changed on the Flexible Lower Partial Denture
The dentist seated the wax try-in and had the patient lift the tongue, swallow, and talk . Notes and photos came back through our WhatsApp group for the case, which has one contact on our side.
Two limits on this round. Wax doesn’t flex like Valplast, and we kept the trial base out of the blocked-out zone . So it tested tooth position, bulk, and strap height. It couldn’t test the path past #18. That had to wait for delivery.
| Item | At try-in | What the dentist asked | Final |
|---|---|---|---|
| Strap lower edge | Caught the floor of the mouth with the tongue up | Raise it | 0.5 mm higher |
| Strap height | 4 mm | Lose the 0.5 mm from the bottom only | 3.5 mm |
| Strap top edge | 2 mm below gum margins, fine | No change | No change |
| #20 arm | Showed when talking | Drop it | 0.5 mm lower |
| #30 cheek side | Patient bit the cheek once | Slim it | 0.5 mm slimmer |
| Bite | Light on both teeth | No change | No change |
Each change had a price. A shorter strap flexes more, so we took it from 2.2 to 2.5 mm thick to make up for some of that. A lower #20 arm leaves less to work with on that side, and the dentist accepted that for the look .
The Finished Flexible Lower Denture
The design goals for this flexible lower denture were one piece, no prep, front gum margins clear, low arms on #20 and #29, and nothing forced into the deep undercut. Final inspection:
| Check | Result |
|---|---|
| Seating on the model | Full seat, no rocking, no lifted edges |
| Lingual flange at #18 | Stops above the deepest undercut, as mapped |
| Strap | 3.5 mm tall, 2.5 mm thick, top edge 2 mm below gum margins |
| Saddle thickness, by caliper | 2.0–2.5 mm, no sudden changes |
| Joins under strong light | No bubbles or cracks where the strap meets the saddles |
| Teeth, under finger pressure | No movement on #19 or #30 |
| Clasp arms, by caliper | Within 0.1 mm of design |
| Articulating film | Light, even marks on both teeth, none in side movements |
What happened at delivery
The path past #18: it went in on the first try, #18 side first, then down on the right . The patient needed two practice runs in the chair .
Adjustments: the #18 arm felt tight, so the dentist used hot water and bending, as Valplast’s clinical techniques describe for a tight clasp . One spot on the flange at #18 got eased with a green stone at the two-day check . That’s the margin we’d left on purpose.
The patient: chewing on both sides again at two weeks, mostly softer foods . Some movement on harder foods, as the dentist had warned . The tongue stopped noticing the strap after about a week .
Still open: a flexible lower denture like this one still carries the sinking risk. These flexible clasps also cover the cervical third of the abutments and the marginal gums, so the dentist set recall visits for abutments, gums, ridge, and fit . This is delivery and two-week feedback , nothing longer.
Sending a Similar Flexible Lower Denture Case
Tipped molar, lingual undercut, patient who won’t accept prep? Send the records first. We offer a pre-shipment feasibility review, and a design is far easier to change before anything’s made.
We need:
A flexible lower denture generally takes 5–7 working days, and a try-in round counts inside that . Design sign-off can add 1–2 days, and courier and customs time are separate.
Who Made It
Our 55-person removable department made this lower flexible partial denture in Istar Dental Lab’s own labs. Istar has four labs in Shenzhen and Huizhou, China, about 460 people, and has been at it since 2012. Nothing gets outsourced. A separate 25-person QC group checks work before it ships, and the removable department handles about 4,000 cases a month in the slow season and about 6,500 at peak.
Istar is an FDA-registered establishment (Registration Number 3039441248), which you can look up in the FDA database, and our labs run an ISO 13485 quality management system. For EU clinics, custom-made partials follow the MDR custom-made device procedure.
Flexible Lower Denture FAQ
Can you reline, repair, or add a tooth to a flexible lower denture later?
Yes, all three, and it’s lab work, because the 2020 review notes that reline resin bonds poorly to this material. Send the appliance, upper and lower models, and a bite record. Valplast’s own FAQ warns the patient may go a few days without the partial, so plan around that.
Can you repair a flexible partial you didn't make?
Yes. Same records as above. We’ll look it over and tell you what we can do with it.
Who decides the design?
The dentist, not the technician. We build to your Rx. If something looks risky, we say so and ask what you’d like. Want a change? We change it. Keep it as is? We make it to the Rx with no risk form to sign, and problems caused by that design, remakes included, aren’t on us.
What's the warranty?
Istar’s warranty on the base is 1 year. A base that won’t seat, lifted edges, badly placed clasps, an off bite, or the wrong gum color get adjusted or remade free. Changing the shade or material later isn’t covered, and neither is going ahead on a poor impression after we’ve warned you. You pay to send a case in, and we pay to ship finished work back, remakes included.
Valplast’s own limited lifetime warranty is separate. It covers breakage of the resin base, not the teeth.
How long does a flexible lower partial denture last?
We don’t put a number on it. Canada’s Drug Agency didn’t find enough follow-up to judge durability over a denture’s lifespan. The American College of Prosthodontists lists triggers for evaluating any removable partial for replacement, such as lost retention or support, a lost abutment, or more than 5 years in function.
Is the resin genuine Valplast?
Yes. We can ship a Valplast Certificate of Authenticity with the case when you need one, and each certificate has a serial number you can register with Valplast.
What should the patient clean it with?
Valplast’s care page calls for a specially designed denture brush, since ordinary toothbrushes can scratch the surface. It also has soaking directions you can pass along.
What other partials do you make?
Acrylic, cast frameworks, and other flexible partials. The full range is on our partial dentures page.
Can you rush it?
Yes, free of charge, if you send us 10 or more cases a month. We guarantee the ship date, not the arrival date, because customs times vary.
How does pricing work?
Prices aren’t on the website. Quotes are itemized to your requirements, not one bundled price.
Send Us Your Next Lower Partial Case
Got a patient who needs a flexible lower denture and an awkward molar in the way? Single trial cases are welcome, and ongoing partnerships suit clinics with a regular case flow. Ship us a test case, request the price list, or book a factory or video visit.