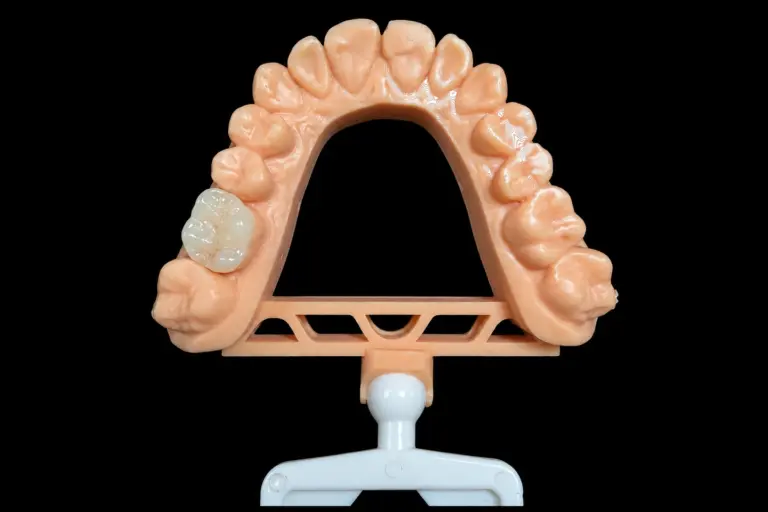
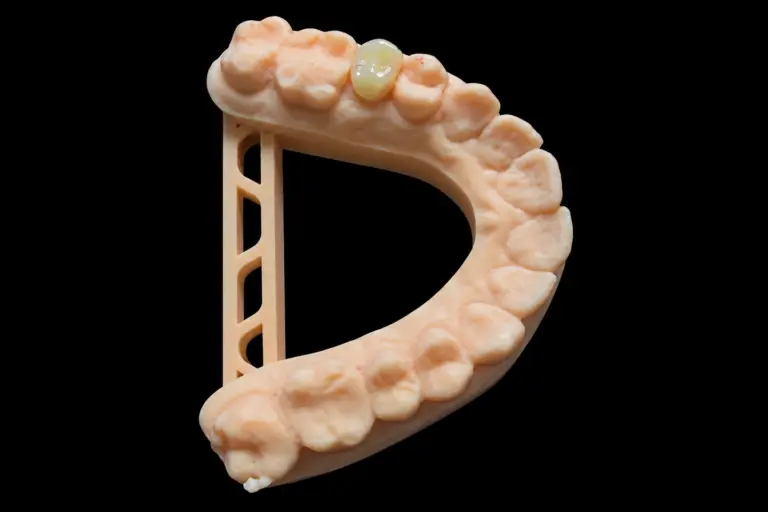
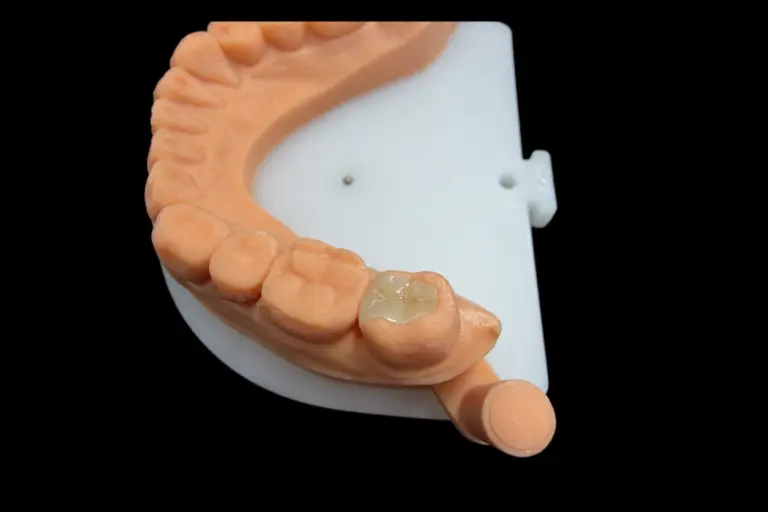
Patient Situation
The patient is an adult in their mid-40s, with no grinding or clenching reported . Both teeth had old amalgams. At a recall visit, the dentist found margin breakdown and decay where the two restorations met .
With the amalgam and decay out, the dentist’s notes and the first scan recorded :
| #29 (lower right second premolar) | #30 (lower right first molar) | |
|---|---|---|
| Old restoration | DO amalgam | MOD amalgam |
| Pulp | Vital | Vital |
| Buccal side | Wall about 2.6 mm thick | Walls about 1.4 mm thick, undermining the mesiobuccal, distobuccal and distal cusps |
| Lingual side | Wall about 2.4 mm thick | Walls about 2.7 mm thick, cusps sound |
| Cavity color | Clean, light dentin | Gray staining on the pulpal floor from the old amalgam |
| Margins | On enamel, box floor 1 mm above the gum | On enamel, mesial box floor right at the gumline |
| Other neighbor | #28, natural and untouched | #31, natural, needs a rebuilt contact |
| Shows in a smile? | Yes, in a normal smile | Buccal margin only, in a wide smile |
Why This Case Needed a Dental Ceramic Inlay and an Onlay
The dentist made each of these calls .
#29 got an inlay
The cavity was wide, but nothing needed covering. A review of ceramic inlays in posterior teeth names excessive isthmus width as a spot where a dental ceramic inlay is a real option over direct composite.
#30 got an onlay
The buccal cusps take load on a lower molar, and their walls were too thin to leave alone. One restorative dentist’s published onlay protocol reduces and covers any cusp under 2 mm thick.
#30 didn't get a crown
The dentist wanted to keep the lingual cusps. That same article cites a preparation study that put tooth removal at 39% for an MOD onlay and 72.3% for a full crown. It’s one study on one prep design, not a general rule, but it shows the kind of difference the dentist was weighing.
Nothing went to metal
The patient asked for tooth-colored work.
What the Dentist Asked For
The Rx and notes on this ceramic inlays and onlays case asked for :
The Technical Problems in This Ceramic Inlays and Onlays Case
One contact, no natural wall to copy
Normally a proximal contact is built against a neighbor that’s already there. Here, the #29 distal box faced the #30 mesial box. Both surfaces would be new. So the contact had no fixed reference, and its height, position and tightness all had to come from the design.
Two pieces that get in each other's way
Each restoration has its own path of insertion, set by its own boxes. If the contact bulges too much, the first piece in blocks the second. A contact that seems fine on a single die can bind once both pieces are on the model, and here it had to clear in both orders.
Same A3, different result
A small dental ceramic inlay has tooth all around it, so it borrows color from the enamel. The onlay on #30 is bigger, with more ceramic, less tooth behind it and a darker background. The same review ties a good dental ceramic inlay match to both the right shade and the right translucency. So one ingot for both teeth wasn’t a safe bet.
Getting enough ceramic over the cusps
A systematic review of ceramic onlays says longevity can improve when the prep allows at least 2 mm of occlusal ceramic, which is where the Rx figure came from. Whether the space was really there was up to the scan.
What We Found on the First Scan
Our team checked the intraoral scans, shade photos and Rx for this porcelain inlay onlay case before any design work. Three things came up :
| What we saw | Why it mattered | What happened |
|---|---|---|
| The #30 mesial box margin was blurred at the gumline, with tissue covering part of it | We’d be guessing at a margin right at the shared contact | We asked for a new scan after retraction |
| 1.5 mm of clearance over the distobuccal cusp of #30 | The Rx figure couldn’t be met there | We sent the dentist three options |
| A 0.2 mm undercut on the lingual wall of the #30 mesial box | It could stop the onlay from seating | Small enough to block out in the design, so we did and told the dentist |
We posted marked-up screenshots in the case’s WhatsApp group the same day .
The clearance options :
The dentist picked the first one, since the patient had to come back for the retraction and rescan anyway .
The Porcelain Inlay Onlay Material: Pressed Lithium Disilicate
Plenty of dentists still write “porcelain inlay onlay” on the Rx. Ivoclar lists IPS e.max Press for both inlays and onlays. We press our e.max inlays and onlays. We don’t mill them. The review notes that inlays made from heat-pressed ceramics tend to show excellent marginal adaptation and good fracture resistance.
Lithium disilicate runs 250–400 MPa in flexural strength, according to the ADA. Those numbers depend on the test method, so don’t read too much into them.
We never swap a material without the client’s OK, written or verbal. If your Rx names a specific brand or batch, we can work to that, and we can provide the brand, origin, batch number and certificates for the material on a case when you ask.
How We Met Each Requirement
| Requirement | What we did | How we checked it |
|---|---|---|
| Material | Designed both restorations together, in one file on the same scan | Material checked against the Rx before pressing |
| Cusp thickness | Built the onlay on the new scan, with 2.0 mm at the distobuccal cusp, the tightest spot | Thickness measured in the design software |
| #29–#30 contact | Set it at the junction of the occlusal and middle thirds, about 2.5 mm wide, and kept the gingival embrasure open | Checked with both pieces on the model |
| #30–#31 contact | Matched the contact height on #31’s mesial surface | Checked on the model |
| Seating order | Rounded the contact surfaces so neither piece has to pass a bulge on the other | Ran it in the software, then seated them both ways on the model |
| Shade | Pressed #29 in a higher-translucency ingot and #30 in a lower one | Compared with the shade photos under standard light |
| Stain masking | Picked the #30 ingot from the photo of the prepared tooth | Checked over a gray-tinted die |
| Design approval | Sent the design for review with nothing pressed yet | Pressing started only after the dentist’s approval |
Making This Ceramic Inlays and Onlays Case, Step by Step
Bonding Notes Sent With the Case
A pressed dental ceramic inlay or onlay gets bonded with resin cement, like Variolink or RelyX Ultimate. We shipped both inner surfaces clean, ready for the dentist’s own etch and silane .
The dentist’s plan was to try both pieces in together, then bond #30 first and #29 second, rechecking the contact in between . That order was their choice. Isolation matters here, too. The review calls proper isolation imperative and highly recommends a rubber dam, and on two adjacent teeth, excess cement has one more place to hide.
The Finished Ceramic Inlays and Onlays
Checking the bite after bonding is normal on this kind of work. The review says it’s often the most practical way to do it, and that chairside finishing can leave a rougher surface. That’s why we try to send porcelain inlay onlay work that needs very little grinding.
Dentist and patient feedback
From the dentist’s message after the bonding visit :
said the extra visit was a fair price for the clearance.
said the bite felt normal by the end of the appointment.
Sending Your Own Ceramic Inlays and Onlays Case
For adjacent preps like these, a few extra things help:
Our lead time for ceramic inlays and onlays is generally 5–7 working days. Simple cases can take 2–3. For the full product range, see our ceramic inlays and onlays, inlays and onlays and e.max dental lab pages.
Who Made It
This ceramic inlays and onlays case went through our CAD design department (about 100 people), our ceramic and metal department (about 70) and a separate quality control team (about 25). They all work inside Istar Digital Dental Lab’s four labs in Shenzhen and Huizhou, China. We’ve been running since 2012, have about 460 employees and don’t outsource any step.
Istar Digital Dental Lab is an FDA-registered establishment (Registration Number 3039441248), and you can look that up in the FDA establishment registration database. Our labs run an ISO 13485 quality management system. For the EU, custom-made devices follow the MDR custom-made device procedure. You’re welcome to visit the factory or book a video tour.
Porcelain Inlay Onlay FAQ
What if my patient grinds or clenches?
Put it on the Rx. We’d increase the occlusal thickness and keep contacts flat and evenly spread. The evidence is mixed: the onlay review linked parafunction with more failure, while a study of 547 glass-ceramic restorations found no greater risk with bruxism.
What if I want a design you've flagged as risky?
We’ll tell you what we see and what you could change. If you still want it, we’ll make it to your Rx. You don’t need to sign anything, but problems that come from that design, remakes included, aren’t on our side.
Which scanners do you work with?
3Shape TRIOS, Medit, iTero, CEREC, Shining3D and Planmeca, plus any scanner that exports open files. iTero and CEREC need to export STL or PLY, since we can’t open their proprietary files.
Do you accept physical impressions?
Yes. Send VPS impressions of the prep and opposing arch with a VPS bite registration. Skip wax bites, because they soften and distort in transit.
Can you make the provisionals?
Yes, in composite or PMMA, including 3D-printed ones. Ask when you send the case.
What warranty comes with a porcelain inlay onlay?
Three years. We remake free of charge for problems on our side, like an open margin, an open contact, a high bite, a restoration that won’t seat or an inaccurate shade. Changing the shade or material afterward isn’t free, and neither is a poor impression we flagged and you asked us to run anyway. You pay to send a case in, and we pay to ship finished work back, remakes included.
Can you rush it?
Rush service is free for clients who send us 10 or more cases a month, for any material or case type. We guarantee the ship date. We can’t guarantee the arrival date, because customs times vary.
How is pricing handled?
We don’t publish prices on the website. Ask for our price list, and we’ll quote each case item by item. Single trial cases are welcome, and ongoing partnerships suit clinics with a regular case flow.
Got Two Adjacent Preps Coming Up?
Send us the scan of your next ceramic inlays and onlays case and ask for a prep check. We’ll look at the margins, the clearance and the shared contact, and tell you what we see before anything gets made.